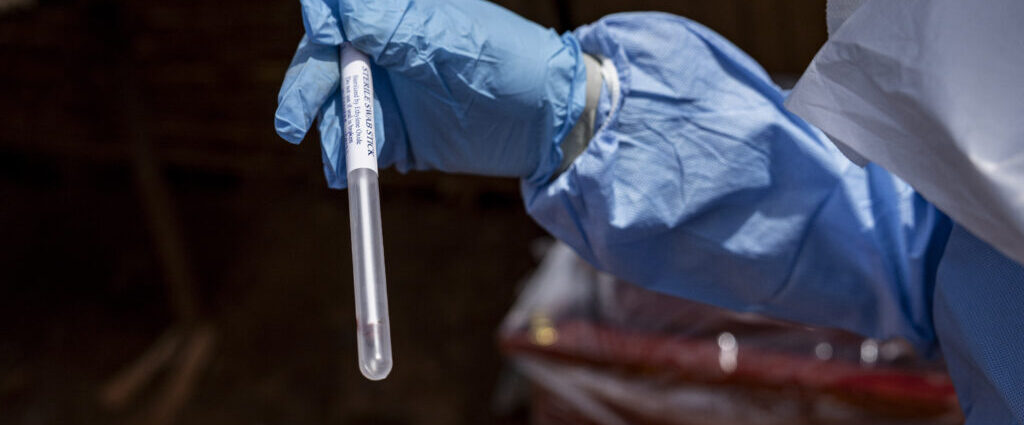
MONGBWALU, Congo — Dr. Richard Lokudu, the medical director of Mongbwalu General Referral Hospital, has received barely any compensation for his work on the front line of one of Congo’s deadliest Ebola virus outbreaks.

Lokudu and several of his colleagues work all day at the hospital treating an influx of patients. Notifications of suspected cases come even late at night.


Read the rest…

This post was originally published here. 

The blockbuster weight-loss drugs known as GLP-1s are doing more than changing waistlines. They are quietly rewiring the American grocery basket, forcing food makers and supermarkets to rethink what they stock, how big the packages are, and which aisles they bet on.

The scale of the behavioral change is striking. According to PwC’s analysis of consumer data from Numerator, GLP-1 users consume 40% fewer calories on average, with dessert consumption down 84% and alcohol use down 33%, while fresh produce intake is up more than 70%. Family grocery baskets are 4% to 6% smaller, and single-person households have seen declines of up to 9%.

That shrinking basket is a real threat to packaged-food giants. Diet changes linked to the drugs could mean up to $12 billion in lost snack sales over the next decade, according to EY-Parthenon estimates, and the industry has stopped treating it as a passing fad. Nearly three dozen companies outside healthcare mentioned GLP-1 drugs or weight loss on their earnings calls so far this year, up from 14 a year earlier, according to LSEG data.

The corporate response is already visible on shelves. Companies from PepsiCo to Coca-Cola and General Mills are focusing on shorter ingredient lists, smaller pack sizes, protein-rich foods, and product reformulations to adapt to shifting demand. The bet is that selling less food per package — but more nutrient-dense food — can offset falling volumes.

For grocers, the change is less about losing customers than about where those customers spend inside the store. GLP-1 users increasingly gravitate toward fresh produce, lean cuts of meat, and other healthier options, meaning shoppers often do not switch stores — they simply shift their spending toward the fresh perimeter departments. That is pushing retailers to make produce, meat, and wellness sections more prominent while expanding protein, fiber, and portion-controlled offerings.

The trend appears likely to grow rather than fade. A Circana report projects that households with GLP-1 users will account for more than one-third of food and beverage sales by 2030, up from about 23% of U.S. households today. “The rise of GLP-1 medications is a huge moment for the CPG industry,” said Sally Lyons Wyatt, Global Executive Vice President at Circana.

Analysts say the disruption is only beginning to be understood. “We’re just starting to scratch the surface on the ripple effects of this type of physiological disruption,” said Ali Furman, PwC’s U.S. Consumer Markets Leader.

The business stakes run from the factory to the checkout counter. Food manufacturers face a generation of customers who simply eat less, retailers must redesign stores around healthier appetites, and even restaurant chains are testing smaller portions and GLP-1-friendly menu options. The companies that adapt fastest — selling smaller, healthier, higher-margin products — may turn a demand shock into an opportunity. Those that continue betting on jumbo bags of chips may find that both the shelves and the shoppers have moved on.

This article is general business reporting, not medical advice. Anyone considering these medications should consult a physician.

JBizNews Desk — Retail & Consumer Goods

© JBizNews.com All Rights Reserved. Reproduction or distribution without written permission is prohibited.

Want to stay on top of the science and politics driving biotech today? Sign up to get our biotech newsletter in your inbox.

Gene therapies can now cure disease, but America still hasn’t figured out how to pay for them. Is there a better way? Also, Novo executives are downplaying a once-coveted obesity drug, Incyte is making a $2 billion blood disease bet, and new data suggest Boehringer’s obesity contender may struggle to stand out in an increasingly crowded market.

The need-to-know this morning

  • Roche is partnering with Nurix Therapeutics to co-develop an experimental antibody treatment that works by degrading, or eliminating, a protein called BTK that is associated with blood cancer and other diseases. 

  • Treeline Biosciences, the developer of early-stage cancer medicines co-founded by biotech entrepreneur Josh Bilenker, is going public via a reverse merger with Standard BioTools. 

Combination of pancreatic cancer drugs from Tango, Revolution leads to high response rate

Revolution Medicines’ experimental pancreatic cancer drug has been the star of the oncology field in recent weeks, with new data showing the medicine produced unprecedented outcomes for patients.

Continue to STAT+ to read the full story…

This post was originally published here. 

This is the online version of STAT’s weekly email newsletter Health Care Inc. Sign up here.

I live in northwest Indiana, and it appears the Chicago Bears are going to put the team’s new stadium here, well outside the actual city of Chicago with almost no public transit and financed completely by Indiana taxpayers. The Bears are successfully pissing off just about everyone — no small feat. Send all Bears thoughts and health care tips my way! bob.herman@statnews.com.

The breastfeeding billing battle

UnitedHealthcare is cutting back on paying for lactation counseling, and the clinicians who provide those services are up in arms, another example of the deepening rifts between providers and insurers.

Continue to STAT+ to read the full story…

This post was originally published here. 

Americans are paying far more to stay insured in 2026, and the increases are landing hardest on the people who buy their own coverage — a squeeze that is already reshaping household budgets and corporate benefit plans alike.

The numbers are stark. According to an analysis by KFF, the nonpartisan health policy research group, premiums on the Affordable Care Act marketplaces are rising by an average of 26% for 2026, with increases of 30% in states using the federal Healthcare.gov marketplace and 17% in states running their own. That is the steepest jump in years and far above anything workers with job-based coverage have seen.

For people with insurance through their employer — the way most Americans get covered — the increase is smaller but still painful. Employer-sponsored insurance costs are projected to rise 6% to 7% in 2026. Virgil Bretz, chief executive of the health technology firm MacroHealth, has noted that such an increase is roughly double the general inflation rate.

What’s driving it comes down to two forces. The first is the simple, relentless rise in the price of medical care. Insurers in one review commonly assumed their medical costs would climb 7% to 8% in 2026, pushed up by expensive hospital care and a wave of costly new drugs. Pricey weight-loss medications known as GLP-1s have become a flashpoint: Blue Cross Blue Shield of Massachusetts said it is dropping coverage of GLP-1 drugs for weight loss in 2026, a move it estimated would reduce its premiums by about 3% — a sign of how much these treatments weigh on costs.

The second force is policy. The enhanced premium tax credits that had cushioned marketplace costs were set to expire, and insurers raised rates partly because they expect higher risk as a result. The consequences for the people who rely on those subsidies are severe. KFF estimated that if the enhanced credits lapse, what subsidized enrollees pay would more than double — a 114% jump, from an average of $888 a year in 2025 to $1,904 in 2026.

The pain is wildly uneven by geography. The average monthly benchmark Silver plan for a 40-year-old reached about $752 nationally, up 21% from a year earlier, but ranged from $480 in Maryland to $1,224 in Vermont. Arkansas led the country with a 67% increase, while a handful of states held increases below 10%, with states that run reinsurance programs generally seeing milder hikes.

The business implications run deep. For employers, a 6% to 7% rise in health costs means higher spending on every worker, money that competes with wages, hiring, and investment. Small businesses, which lack the bargaining power of large corporations, tend to feel it most and are likeliest to pass the cost to employees through higher payroll deductions or skinnier plans. The people most exposed are the roughly 2.4 million unsubsidized marketplace enrollees — often self-employed workers or early retirees — who absorb the full increase.

There is a broader economic risk, too. When coverage gets too expensive, healthy people drop it, leaving insurers with a sicker, costlier pool and pushing premiums even higher — the kind of cycle the industry has long feared. The Congressional Budget Office has estimated the number of uninsured Americans could rise by roughly 3.8 million a year if the enhanced subsidies are not extended, which would shift more unpaid medical bills onto hospitals and, ultimately, onto everyone else’s premiums.

For households already stretched by high grocery and energy prices, a double-digit jump in the cost of staying insured is one more strain on a budget that has little give left. And for the companies that provide coverage to most working Americans, 2026 is shaping up to be the year health benefits stop being a manageable line item and start forcing hard choices.

This article is general business reporting, not medical or financial advice; coverage decisions are best made with a licensed professional.

JBizNews Desk — Health Care

© JBizNews.com All Rights Reserved. Reproduction or distribution without written permission is prohibited

Revolution Medicines’ experimental pancreatic cancer drug has been the star of the oncology field in recent weeks, with new data showing the medicine produced unprecedented outcomes for patients. 

Its next act — this time as a co-lead — was revealed Monday.

Tango Therapeutics said that in an early-stage clinical trial, a combination of its drug vopimetostat along with Revolution’s daraxonrasib led to a durable responses in the large majority of pancreatic cancer patients who received both medicines. 

Continue to STAT+ to read the full story…

This post was originally published here. 

A new class of medicines is transforming health care. Gene therapies can now cure diseases like sickle cell with a single treatment, but they come with a price tag that would have been unthinkable a decade ago — often $2 million or more per patient.

In a way, this cost makes sense: These are potential cures that can avoid years of hospitalizations, complications, and lost productivity. In many cases, they concentrate decades of value into a single intervention.

Read the rest…

This post was originally published here. 

The horses in America are getting fat. They are trying to tell us something.

Fifty-one percent of mature light-breed horses in the United States are obese — a rate that ranks among the world’s highest, slightly above Britain and nearly twice that of Australia or Denmark. That figure comes from a peer-reviewed prevalence study, and it sits alongside a number that should give any clinician pause: The U.S. also leads the G7 in human obesity. The same country. The same epidemic. A completely different species.

Read the rest…

This post was originally published here. 

BOSTON — Carlton Haynes hugged his left knee, pulling it toward his shoulder as hard as he could. He was desperate to blunt the pain shooting from an open, oozing wound on his right shin. Anahita Dua, a vascular surgeon leading an unusual clinic created by Massachusetts General Hospital that Saturday, told him he was going to the ER and then the OR, where she would remove damaged skin and treat the wound. 

Without this stopgap measure, she warned him, he’d almost certainly need amputation. OK, he said, but first he wanted a smoke. 

Read the rest…

This post was originally published here. 

You’re reading the web edition of STAT’s ADA in 30 Seconds newsletter, from the American Diabetes Association’s annual conference. 

Welcome to the third and final edition of STAT’s ADA in 30 Seconds newsletter.

Elaine Chen starts us off with updates on the competitive climate for obesity drugs and I’m relaying insights on eating disorders, new word on a BCG vaccine, and a clarification from ADA on Friday’s police incident.

Continue to STAT+ to read the full story…

This post was originally published here. 

New data on Boehringer Ingelheim’s obesity candidate suggest the drug may be helpful in cutting liver fat, but it’s not clear how competitive the treatment would be since it appears less efficacious and less tolerable than drugs on the market.

In a Phase 3 obesity trial, patients on the highest dose of the weekly injectable, called survodutide, lost 13% of their weight after 76 weeks, compared with 5% in the placebo group, according to data presented Sunday at the annual meeting of the American Diabetes Association and published in the New England Journal of Medicine. That’s lower than the rate of weight loss seen in pivotal trials of Novo Nordisk’s Wegovy and Eli Lilly’s Zepbound. 

Patients on survodutide, which targets the GLP-1 and glucagon hormones, did lose up to 63% of their liver fat, compared with 25% in the placebo group. Glucagon-targeting drugs are thought to be particularly helpful in cutting liver fat, since there are glucagon receptors in the liver.

Continue to STAT+ to read the full story…

This post was originally published here. 

NEW YORK— Americans are quietly eating less, and it’s starting to show up on the books of the country’s biggest food companies. The cause isn’t a recession or the latest diet fad. It’s a class of weight-loss drugs—Ozempic, Wegovy, Mounjaro, and Zepbound—that switch off hunger. About one in eight U.S. adults now takes one, and this spring the first cheap, easy-to-swallow pill versions reached pharmacy shelves.

Wall Street is already doing the math on the fallout. J.P. Morgan projects these drugs could erase $30 billion to $55 billion in annual U.S. food and beverage sales by the early 2030s, as users take in about 21% fewer calories and spend roughly 31% less at the grocery store.

Here’s why that number is so big.

The drugs were built to treat diabetes, but they also quiet the brain’s hunger signals, so people feel full sooner and snack less. In April, Eli Lilly won approval for Foundayo, the first weight-loss pill that can be taken without food or water restrictions, and it’s now reaching retail pharmacies. Novo Nordisk has a pill out, too. Cheaper, needle-free options are expected to pull millions more people onto the drugs—J.P. Morgan sees the U.S. user base climbing toward 25 million to 30 million people by 2030, up from about 10 million in 2025.

When that many people eat less, the grocery cart changes.

A Cornell University study tracked roughly 150,000 households and found that within six months of starting the drugs, families cut grocery spending by an average of 5.3%. Higher-income households cut more than 8%. Spending at fast-food restaurants and coffee shops fell about 8%, too. The cuts landed right where food companies make some of their best margins: sweets and salty snacks dropped around 10%. Yogurt, meanwhile, went up. People are swapping chips and candy for protein and fiber.

This is the part that worries Big Food, and the biggest brands are scrambling.

Conagra, which makes Healthy Choice meals, slapped a “GLP-1 friendly” label on more than two dozen of its frozen dinners. Nestlé launched a line called Vital Pursuit aimed directly at people taking the drugs. The shift is now significant enough that nearly three dozen non-healthcare companies discussed GLP-1 medications on earnings calls earlier this year, up from just 14 companies a year earlier.

Restaurants are rewriting menus, too. Olive Garden, owned by Darden Restaurants, added a lighter-portions section. The Cheesecake Factory rolled out smaller bowls and smaller meals. Shake Shack launched a “Good Fit Menu” featuring lettuce-wrapped burgers with up to 52 grams of protein. Even McDonald’s says it is testing high-protein, GLP-1-friendly items as it prepares for more customers with smaller appetites.

The math behind those changes is difficult for some chains. Bank of America found that snacking accounts for roughly 12% of sales at limited-service restaurant chains such as McDonald’s and Taco Bell—and snacking is exactly what these drugs are designed to reduce.

Not everyone is losing. The same medications reducing food consumption are generating enormous growth elsewhere. J.P. Morgan expects the global market for these drugs to reach $200 billion by 2030. Pfizer paid $10 billion last year to acquire a drugmaker developing its own version after outbidding seven competing buyers. And Washington is leaning in: a new Medicare and Medicaid pilot program would cap costs for some patients at $50 per month, potentially expanding usage further.

In the short run, the hit to food companies remains modest—a fraction of overall sales. The industry still has time to adjust, and some companies are already finding growth opportunities in high-protein snacks, nutrition-focused products, and healthier prepared meals.

But the long-run signal is becoming difficult to ignore. For the first time, a medicine—not a tax, not a recession, and not a public-health campaign—is changing how much the country eats. The companies that spent a century getting Americans to eat more now have to figure out how to make money when millions of their best customers simply want less.

JBizNews Desk — New York

© JBizNews.com All Rights Reserved. Reproduction or distribution without written permission is prohibited.

You’re reading the web edition of STAT’s ADA in 30 Seconds newsletter, from the American Diabetes Association’s annual conference. Sign up here

Welcome back! The American Diabetes Association annual conference is in full swing with news about old and new approaches to treating diabetes.

Buckle in for a day 2 recap.

Continue to STAT+ to read the full story…

This post was originally published here. 

Eli Lilly has already established that its next-generation obesity drug can lead to highly rapid weight loss. Researchers disclosed new data Saturday that provide more details on the safety and tolerability of the closely-watched therapy.

Lilly previously said that in one late-stage study, called TRANSCEND-T2D-1, retatrutide helped people with diabetes lower blood sugar and lose a significant amount of weight, which is notable since those who have diabetes tend to lose less weight on treatment than those who don’t.

New data showed that seven out of the 403 participants who received retatrutide experienced arrhythmias (irregular heart beats), and three treated participants experienced major cardiovascular complications, compared with none in the placebo group. The data were presented at the annual meeting of the American Diabetes Association and published in the Lancet.

Continue to STAT+ to read the full story…

This post was originally published here. 

Detailed data from a mid-stage study offered further evidence that the obesity drug Pfizer acquired from the biotech Metsera could be dosed monthly. But it’s not clear how competitive the treatment would be against weekly injectables on the market and in development that may lead to greater weight loss.

In the study, called VESPER-3, patients with obesity took weekly doses of the drug, called berobenatide, for 12 weeks and then transitioned to higher monthly doses out to 28 weeks. By then, patients lost up to 12.1% of their weight, when analyzing just those who stayed on treatment, as Pfizer previously reported. 

New data presented at the annual meeting of the American Diabetes Association on Saturday show that when patients transitioned from weekly to monthly dosing, the rate of weight loss continued at a similar pace; they had not yet hit a plateau by 28 weeks. That’s a promising sign, but the rate of weight loss at 28 weeks was still less than what was seen at a similar time point in the pivotal trial of Eli Lilly’s Zepbound.

Continue to STAT+ to read the full story…

This post was originally published here. 

By the time the world began responding to the West Africa epidemic in 2014, which killed more than 11,000 people before it ended in 2016, there were 40 to 50 suspected cases.

The current outbreak in the Democratic Republic of the Congo had approximately 10 times that number by the time the response started. Three weeks in, it has spread from three health zones to 25, with new areas added almost daily. National, provincial, and local health staff are responding intensively, but fewer than half of known contacts are being traced nationwide, laboratories are backlogged, no Ebola treatment center is ready, few health workers have been trained, there’s insufficient protective equipment for health workers and few medications for patients, and burial teams have come under attack.

Read the rest…

This post was originally published here. 

Below is a lightly edited, AI-generated transcript of the “First Opinion Podcast” interview with Cory Anderson and Braxton Mitchell. Be sure to sign up for the weekly “First Opinion Podcast” on Apple Podcasts, Spotify, or wherever you get your podcasts. Get alerts about each new episode by signing up for the “First Opinion Podcast” newsletter. And don’t forget to sign up for the First Opinion newsletter, delivered every Sunday.

Torie Bosch: Last fall, there was a flurry of interest in the Amish and health after President Trump repeated a common claim among vaccine critics: that the Amish don’t vaccinate and don’t get autism. It’s much more complicated than that, though — and it’s far from the only interesting and consequential question about the Amish and public health.

Read the rest…

This post was originally published here. 

NEW YORK — The Ebola outbreak in Central Africa could grow to 20,000 cases or more, depending on how quickly infected people are isolated to slow the spread, according to a new analysis by U.S. health officials.

The Centers for Disease Control and Prevention published a range of scenarios generated by computer models Friday, spanning from 10,000 cases to more than 20,000. If accurate, a worst-case scenario could approach the worst Ebola outbreak in history, the West Africa epidemic in 2014-2016 — which resulted in more than 28,000 reported cases and more than 11,000 deaths.

Read the rest…

This post was originally published here. 

You’re reading the web edition of STAT’s ADA in 30 Seconds newsletter from the American Diabetes Association’s annual conference. Sign up here

This is Elizabeth Cooney saying hello from New Orleans, where the weather is warm, the conference center is cool, and debates can be fiery. Welcome to the first of three ADA in 30 newsletters, in which my colleague Elaine Chen and I curate some of the news and analyses circulating here near the banks of the mighty Mississippi.

First up, thoughts from Rick Woychik, a senior adviser to NIH chief Jay Bhattacharya who subbed for him as keynote speaker, plus some background from our STAT colleague Anil Oza. Then, what the weekend will bring.

If you are here too, come say Hi, or reach me at elizabeth.cooney@statnews.com.

Continue to STAT+ to read the full story…

This post was originally published here. 

NEW ORLEANS — A senior adviser to the leader of the National Institutes of Health opened his speech to a national gathering of diabetes researchers with a full-throated endorsement of the Make America Healthy Again movement. Then, during the fireside chat that followed, he withstood sustained cheers for criticism of deep funding cuts to the nation’s biomedical research enterprise that he was asked to explain.

“I could have written the MAHA agenda,” Richard Woychik, who works closely with NIH Director Jay Bhattacharya, said Friday, recalling when he first learned last October of the policy embraced by Health Secretary Robert F. Kennedy Jr.  

Read the rest…

This post was originally published here. 

Thousands of Health and Human Services Department staff who shape policy, including on public health, federal health insurance programs, and health data privacy, have had their employment status changed to a designation that makes it easier for them to be fired, and thus makes them more vulnerable to political pressure from the White House. 

The reclassification of roughly 8,000 employees across the federal government, outlined in an executive order President  Trump issued late Wednesday, also impacts some National Institutes of Health workers who oversee grant funding.

On the whole, health policy experts said, the shift toward a more politicized workforce is part of a broader goal of the Trump administration to shift power away from Congress and toward the executive branch. The policy, known as “Schedule F,” dates back to Trump’s first administration and would create a new class of federal employees that are not political appointees, but could be fired at will.

Continue to STAT+ to read the full story…

This post was originally published here. 

Americans are increasingly frustrated about being blocked off from care, which results in worse health outcomes and financial stress, per the new study. Still, insurers generally defend their claims review processes and argue improper denials aren’t their fault.

This post was originally published here. 

When I deployed to Sierra Leone during the 2014-2016 West Africa Ebola epidemic, I understood the risks.

Every physician, nurse, epidemiologist, laboratorian, and aid worker who enters an Ebola outbreak does. We know that despite rigorous training and infection prevention measures, exposures can occur. We know that outbreaks unfold in difficult environments, often amid insecurity, fragile health systems, and limited resources. We know that if we become ill, our lives may depend on access to highly specialized medical care.

Read the rest…

This post was originally published here. 

And so, another working week will soon draw to a close. Not a moment too soon, yes? This is, you may recall, our treasured signal to daydream about weekend plans. Our agenda includes promenading with the official mascots, catching some live musical vibes, and looking in on the Pharmalot ancestor. We also hope to squeeze in yet another listening party, where the rotation will likely include this, this, this, this and this. And what about you? Summer is closing in so this may be an opportunity to book a getaway, find some fab beach gear, or compile a challenging reading list. You could hit the pause button and catch up on your naps. Or maybe there is time to hang with someone special. Well, whatever you do, have a grand time. But be safe. Enjoy, and see you soon. …

Leaders at the U.S. Food and Drug Administration listened to criticisms and recommendations for how to move forward with a speedy drug review program put in place by former FDA commissioner Marty Makary, STAT tells us. The listening session, held on the FDA’s White Oak Campus, featured 17 speakers representing patient groups, drug companies, and academic organizations. Some had positive feedback, particularly those whose drugs have already been approved through the program. But most asked the agency to pause the program, and then bring it back through normal regulatory procedures that require public feedback. 

Meanwhile, the FDA has launched a safety study of the mifepristone abortion pill, a step that could pave the way for the Trump administration to restrict how it is distributed and used, The Wall Street Journal reports. The study marks a victory for antiabortion groups and Republican members of Congress, who have demanded action from the administration to crack down on the pill’s use. In recent months, antiabortion allies had lost patience with assurances from administration officials that a study would be conducted. The effort is expected to take about six months, meaning it likely will not be completed before the midterm elections.

Continue to STAT+ to read the full story…

This post was originally published here. 

Get your daily dose of health and medicine every weekday with STAT’s free newsletter Morning Rounds. Sign up here.

The American Diabetes Association’s annual conference starts today. STAT’s Elizabeth Cooney will be embedded in New Orleans to file three ADA in 30 newsletters, with help from Elaine Chen covering newsworthy items on the weekend’s agenda. If you want a newsletter to follow along, sign up here.

Read the rest…

This post was originally published here. 

Want to stay on top of the science and politics driving biotech today? Sign up to get our biotech newsletter in your inbox.

Even though RevMed’s experimental pancreatic cancer drug, daraxonrasib, hasn’t yet achieved approval, it is available through an expanded access program. But that doesn’t mean getting it is easy.

Also, the FDA’s voucher program spearheaded by erstwhile chief Marty Makary could be in for a makeover.

Continue to STAT+ to read the full story…

This post was originally published here. 

By JBizNews Desk

Federal officials cut off funding to Hawaii’s Medicaid anti-fraud program on Thursday, June 4, making it the first state formally penalized in the Trump administration’s nationwide crackdown—and a warning shot to every other state in the country.

Federal Trade Commission Chairman Andrew Ferguson, a co-chair of the White House anti-fraud task force, announced the decertification at a press conference in Ohio, saying Hawaii had shown an “abject failure” to enforce state and federal law against fraud.

The move marks the first time a state has lost certification under the administration’s escalating effort to force stricter Medicaid fraud enforcement nationwide.

Why It Matters

Every state that participates in Medicaid is required to maintain a Medicaid Fraud Control Unit (MFCU), typically overseen by the state attorney general, to investigate fraud and abuse involving Medicaid funds.

Federal officials warned that ineffective enforcement can put broader federal Medicaid funding at risk.

That means the consequences may extend beyond Hawaii’s fraud unit itself.

The administration is signaling that states receiving billions in federal health-care dollars must actively police fraud or risk losing federal support.

Why Hawaii Was Targeted

Federal officials cited Hawaii’s performance as the worst in the nation.

According to the administration, Hawaii’s Medicaid Fraud Control Unit received approximately $3 million annually in federal funding yet produced zero criminal Medicaid fraud indictments between 2022 and 2025.

During the same period:

  • Medicaid enrollment reportedly increased roughly 40%
  • Medicaid funding increased approximately 27%
  • No fraud-related criminal indictments were filed

March Bell, Inspector General for the U.S. Department of Health and Human Services, notified Hawaii Attorney General Anne Lopez of the decertification, citing the lack of arrests, prosecutions, and convictions.

A Warning to Every State

The action follows months of pressure from Washington.

In May, federal officials sent notice letters to the attorneys general of all 50 states, demanding stronger cooperation in investigating and prosecuting Medicaid fraud.

Hawaii is simply the first state to face direct consequences.

Administration officials say additional states could face similar actions if they fail to strengthen fraud enforcement efforts.

The Ohio Case That Helped Trigger the Announcement

The decertification announcement came alongside a broader federal fraud sweep unveiled Thursday.

According to the Justice Department, investigators uncovered a multimillion-dollar Medicaid scheme involving children’s mental-health services in Ohio.

Authorities allege that services were medically unnecessary, improperly billed, or never provided as represented.

Investigators say that after one provider lost credentialing with the Ohio Department of Mental Health and Addiction Services, claims continued to be submitted through another entity.

Federal authorities seized approximately:

  • $469,000 from three bank accounts
  • 14 vehicles worth roughly $800,000

Among the seized vehicles:

  • Six Mercedes-Benz vehicles
  • Bentley
  • BMW
  • Jaguar
  • Maserati
  • Two Land Rovers
  • GMC
  • McLaren

Acting Attorney General Todd Blanche announced the prosecutions and said the FBI will launch a new “Most Wanted Fraudsters” list as part of the broader initiative.

Not All States Are Being Treated the Same

While Hawaii became the first state penalized, administration officials highlighted states they view as models for cooperation.

Ferguson specifically praised Ohio Attorney General David Yost, citing recent charges against 14 individuals connected to approximately $50 million in alleged fraud schemes.

The message from Washington was clear:

States that actively cooperate with federal investigations are being publicly recognized, while those that fail to do so face increasing scrutiny.

What It Means for Health-Care Providers

The crackdown has major implications for several sectors of the health-care industry.

Federal investigators are focusing heavily on:

  • Behavioral health providers
  • Children’s mental-health programs
  • Home-health agencies
  • Hospice providers
  • Durable medical equipment suppliers

These sectors are often viewed by regulators as higher-risk because billing can be difficult to verify and new providers can enter the market relatively quickly.

Companies operating in these areas face:

  • Increased credentialing reviews
  • Greater audit risk
  • Potential payment freezes
  • Possible removal from Medicaid programs

State governments also face growing pressure because Medicaid relies heavily on federal funding support.

Critics Push Back

The administration’s approach has drawn criticism.

In April, the Centers for Medicare & Medicaid Services acknowledged to The Associated Press that it had made significant errors in data used during a fraud investigation involving New York.

Several Democratic governors have argued that portions of the broader enforcement campaign are politically motivated.

Supporters counter that Medicaid fraud remains a serious national problem.

Administration officials have cited estimates placing annual Medicaid fraud losses as high as $100 billion, pointing to weak provider verification systems and years of inadequate enforcement in some states.

The Bigger Message

What makes Thursday’s action significant is that federal officials moved beyond warnings.

Until now, Washington largely relied on letters, audits, payment delays, and public pressure.

By decertifying Hawaii’s Medicaid Fraud Control Unit, the administration demonstrated a willingness to impose direct penalties.

With warning letters already sent to every attorney general in the country, Hawaii has become the first example of what federal officials say can happen when states fail to meet enforcement expectations.

JBizNews Desk — Healthcare & Government

© JBizNews.com All Rights Reserved. Reproduction or distribution without written permission is prohibited.

In 2021, the federal office charged with ensuring that the vast research enterprise bankrolled by the Department of Health and Human Services keeps study participants safe, received a report of a death by suicide involving a person enrolled in a study testing a treatment for depression and reduced mobility. 

Once the Office of Human Research Protections started looking into the death at the New York State Psychiatric Institute, it found problems that spread far beyond that one study, including failures in how the institute’s ethics board reviews proposed research. “We saw, holy smokes, this whole institution has issues,” said Lisa Buchanan, then director of the OHRP’s compliance division. The investigation became all-consuming. “It was probably 60-70% of our time,” she said.

Read the rest…

This post was originally published here. 

Americans who have high-risk exposures to Ebola in the current outbreak in Central Africa will have access to an antibody treatment that has shown great promise in animal testing but hasn’t yet undergone a clinical trial to show whether it is efficacious in people, the Department of Health and Human Services confirmed Thursday.

The antibody treatment, known as MBP-134, is made by San Diego-based Mapp Biopharmaceuticals, with funding from the Biomedical Advanced Research and Development Authority, an agency within HHS that helps develop medical countermeasures for rare and emerging diseases, and biological threats.

Read the rest…

This post was originally published here. 

WASHINGTON — Leaders at the Food and Drug Administration on Thursday listened to criticisms and recommendations for how to move forward with a speedy drug review program put in place by former FDA commissioner Marty Makary. 

The listening session, held on the FDA’s White Oak Campus, featured 17 speakers representing patient groups, drug companies, and academic organizations. Some had positive feedback, particularly those whose drugs have already been approved through the program. But most asked the agency to pause the program, and then bring it back through normal regulatory procedures that require public feedback. 

Makary launched the Commissioner’s National Priority Voucher program about a year ago, offering one- to two-month FDA reviews to companies that could prove their drugs “align with national priorities.” The priorities, which included addressing health crises and delivering innovative cures, were vague. Critics worried the process was vulnerable to political interference.

Continue to STAT+ to read the full story…

This post was originally published here. 

Otsuka’s Voyxact slowed the loss of kidney function after one year in patients with a chronic autoimmune kidney disease, but the benefit was less than expected and left room for competing treatments to perform better. 

In a Phase 3 study, patients with IgA nephropathy, or IgAN, who received injections of Voyxact saw their kidneys lose function at an annualized rate of 3 points over one year compared to an annualized function loss of 7.6 points over one year for patients receiving a placebo, the Japanese drugmaker reported Thursday. 

Kidney function was assessed with a lab test, called eGFR, that measures how well kidneys filter waste from the blood. 

Continue to STAT+ to read the full story…

This post was originally published here. 

Why did oncologists give a standing ovation to a data presentation on Revolution Medicines’ pancreatic cancer drug, daraxonrasib? Why did biotech stocks perform so badly this week? And are concrete beaches better than normal beaches?

We discuss all that and more on this week’s episode of “The Readout LOUD,” STAT’s biotech podcast.

Read the rest…

This post was originally published here. 

The Supreme Court unanimously ruled that Hikma Pharmaceuticals did not infringe patents held by Amarin in a decision that makes generic drugmakers less vulnerable to lawsuits over so-called skinny labels.

The ruling overturned a lower court decision that sided with Amarin. Generic drugmakers had argued that, if the Supreme Court also ruled in favor of Amarin, they would be discouraged from making and selling lower-cost versions of brand-name medicines, which would maintain higher prices for prescription drugs.

At issue is skinny labeling, which refers to moves by generic companies that seek regulatory approval to market a medicine for a specific use, but not other patented uses for which a brand-name drug is prescribed. For instance, a generic drug could be marketed to treat one type of heart problem but not another. In doing so, the generic company seeks to avoid lawsuits claiming patent infringement.

Continue to STAT+ to read the full story…

This post was originally published here. 

Amy Johnston is distraught and readily admits that she is “grasping at straws.”

Diagnosed last year with pancreatic cancer, she has had chemotherapy and surgery and is now enrolled in a clinical trial hoping to delay progression of the disease. By the end of this month, she expects to know if the treatment is working; if it’s doesn’t, she and her physician plan to seek access to  another drug that, while still technically experimental, is causing a sensation.

The drug, called daraxonrasib and developed by Revolution Medicines, nearly doubled overall survival time in pancreatic cancer patients in a clinical trial. It is now being offered through an expanded access program, which allows critically ill people to receive an experimental medicine outside of such a study.

But for Johnston and other patients, the excitement has come with anxiety. On one hand, there is optimism that the treatment — expected to be approved as a second-line therapy — can prolong their lives. Yet there is so much interest and demand that patients are trepidatious about when they might get the drug or if there will be enough to go around.

“This is such a small company, and I worry their production is not able to keep up with the need,” said Johnston, a 35-year-old office administrator and mother of three young children who lives in Gilbertsville, Pa. “Who receives it first? Will it be for those who the drug is the last resort? It’s a good idea but how early can you get it to people?

Continue to STAT+ to read the full story…

This post was originally published here. 

Many adults are sharing device data with providers too. But users are typically healthier and wealthier, suggesting people who could benefit the most from health monitoring are less likely to adopt the tools, according to Rock Health.

This post was originally published here. 

You’re reading the web edition of D.C. Diagnosis, STAT’s twice-weekly newsletter about the politics and policy of health and medicine. Sign up here to receive it in your inbox on Tuesdays and Thursdays.

Former New York congressman George Santos is under investigation (again). This time for insider trading. Chelsea Cirruzzo here, filling in for John. Send news tips and insider info (kidding!) to chelsea.cirruzzo@statnews.com or chelseacirruzzo.42 on Signal.

RFK Jr.’s second year as America’s health czar

As a favorite Trump surrogate, health secretary Robert F. Kennedy Jr. has spent the first half of the year crisscrossing the country — munching on vegetables at a regenerative farm in Ohio, meeting with Wisconsin dairy farmers, witnessing a robotic arm perform open-heart surgery at the Cleveland Clinic.

Continue to STAT+ to read the full story…

This post was originally published here. 

MINNEAPOLIS — Medtronic, the world’s largest medical-device maker, delivered its strongest annual revenue growth in a decade Wednesday, driven by surging demand for heart procedures and newer cardiovascular technologies that are helping patients live longer and healthier lives.

The company reported fiscal fourth-quarter revenue of $9.8 billion, up 9.9% from a year earlier and ahead of Wall Street expectations. Adjusted earnings came in at $1.55 per share, capping what management described as one of the strongest years in recent company history.

Even if consumers have never heard of Medtronic, many have likely benefited from its products. The company manufactures pacemakers, implantable defibrillators, insulin pumps, surgical instruments, spinal implants, and neurological devices used by hospitals and physicians around the world.

Because of its enormous presence across healthcare, Medtronic is often viewed as a bellwether for the broader medical-technology industry.

The biggest growth story this quarter came from the company’s heart business.

Revenue from Cardiac Ablation Solutions, which includes devices used to treat irregular heart rhythms such as atrial fibrillation, surged 78% globally and 124% in the United States. The broader cardiovascular division grew approximately 10%, while Medtronic’s surgical business posted a solid 5% increase.

Geoff Martha, Chairman and Chief Executive Officer, credited expanding patient access and strong adoption of newer therapies for the company’s performance.

The results arrive as healthcare providers continue seeing rising demand from aging populations that require more cardiovascular treatment, chronic-disease management, and surgical procedures.

For investors, Medtronic delivered another important milestone.

The board approved a dividend increase to $0.72 per share quarterly, marking the company’s 49th consecutive year of dividend growth.

Few public companies can claim nearly half a century of uninterrupted dividend increases.

The consistency reflects Medtronic’s ability to generate significant cash even during periods of economic uncertainty.

For the full fiscal year, the company generated more than $7.3 billion in operating cash flow and approximately $5.4 billion in free cash flow, giving management ample flexibility to invest in future growth while rewarding shareholders.

The company is also expanding through acquisitions.

Earlier this year, Medtronic agreed to acquire SPR Therapeutics for up to $650 million, strengthening its position in the growing market for non-opioid pain management. The acquisition reflects increasing demand for alternatives to traditional pain medications.

Meanwhile, Medtronic continues investing heavily in robotic surgery through its Hugo surgical platform as it seeks to challenge industry leader Intuitive Surgical and its widely used da Vinci system.

Looking ahead, management forecast organic revenue growth of 6.75% to 7.25% for the new fiscal year, suggesting confidence that current momentum can continue.

For the broader healthcare industry, the message is encouraging. Hospitals remain busy, demand for advanced procedures remains strong, and patients continue seeking treatments that improve quality of life.

For shareholders, the story is equally straightforward.

A company that helps keep hearts beating, raises its dividend for nearly five decades, and just delivered its fastest growth in ten years appears to be doing exactly what investors hope a healthcare leader will do.

Wall Street — JBizNews Desk

© JBizNews.com All Rights Reserved. Reproduction or distribution without written permission is prohibited.