The father cradled his newborn daughter as we reviewed routine infant care. Her mother, still recovering from childbirth, joined by video from home. He held his daughter with the tentative confidence and unmistakable love of a first-time parent. As we wrapped up our visit, he shook his head and said, “I can’t believe I have to go back to work tomorrow.”

As a pediatrician, I am unfortunately familiar with this type of story. Parents want to be present during the first days of their children’s lives. Too often, they cannot afford to be — especially fathers.


Read the rest…

This post was originally published here. 

Over a dozen states now have laws enhancing their oversight of private equity deals in health care. A new report says that’s putting a crimp in dealmaking. 

Physician practice management is on track to see about half the number of deals this year as it did in 2025. Investments in the businesses, which run clinics’ billing and operations, have plummeted from a high of 851 deals in 2021 to just 105 in the first half of 2026, according to new data from PitchBook. 

“It’s certainly been a big decrease,” said Paul Pitts, a partner with Reed Smith who works with health care providers. 

Continue to STAT+ to read the full story…

This post was originally published here. 

A psychiatric drug unlike anything currently approved in the United States just cleared a major hurdle.

Definium Therapeutics said Wednesday that a single dose of its LSD-based tablet significantly reduced symptoms of generalized anxiety disorder within days, delivering a major Phase 3 victory that could put the company on a path toward the first FDA-approved LSD-based treatment for anxiety.

The drug, DT120, is a pharmaceutical-grade form of lysergide — better known as LSD — delivered as a tablet that dissolves in the mouth. Unlike conventional anxiety medicines that patients may take every day for months or years, participants in Definium’s trial received one 100-microgram dose under medical supervision.

The effect appeared rapidly.

Patients receiving DT120 showed statistically significant improvement shortly after treatment, with the benefit becoming evident within days following the single administration. The study continued tracking patients for 12 weeks and found that the treatment advantage remained at the study’s final measurement.

That distinction matters: patients did not take the pill for 12 weeks. They took it once.

One Dose Produces Major Phase 3 Result

The Voyage trial enrolled 214 adults ages 18 to 74 with generalized anxiety disorder at roughly 35 U.S. clinical sites.

Patients began the study with moderate-to-severe anxiety and were randomly assigned to receive either DT120 or placebo.

At the study’s primary endpoint, patients receiving DT120 experienced an average 11.6-point reduction on the Hamilton Anxiety Rating Scale, compared with a 6.2-point reduction for placebo.

That produced a 5.4-point advantage over placebo, comfortably clearing the trial’s statistical threshold and giving Definium the positive Phase 3 result investors and regulators were waiting for.

The individual patient results were equally striking.

About 43% of patients receiving DT120 cut their anxiety symptoms by at least half, compared with 16% in the placebo group.

And 14% of patients receiving DT120 reached remission, versus 4% receiving placebo.

Definium said the drug was generally well tolerated and the trial met its primary endpoint and all key secondary efficacy endpoints.

A Different Way to Treat Anxiety

What makes DT120 potentially groundbreaking is not simply that LSD reduced anxiety.

It is the possibility that a chronic psychiatric condition normally managed with daily medication could instead be treated with a single supervised dose producing rapid and lasting improvement.

Many conventional antidepressant and anti-anxiety medicines must be taken every day and can take weeks before patients know whether they are working. Patients may cycle through several medications before finding one that helps.

Definium is proposing a fundamentally different model.

The patient comes to a qualified medical facility, receives a single tablet, remains under supervision while the psychedelic effects wear off and then goes home. No daily prescription follows from that treatment session.

And unlike some psychedelic programs being developed elsewhere, Definium is not requiring psychotherapy to accompany the drug, potentially making the treatment easier for clinics to administer and insurers to reimburse if it eventually reaches the market.

There is currently no FDA-approved LSD medicine for generalized anxiety disorder.

That means DT120, if it successfully completes development and wins regulatory approval, could create an entirely new category of psychiatric treatment.

The FDA has already granted the drug Breakthrough Therapy designation for generalized anxiety disorder, a designation intended to accelerate development and regulatory review of medicines showing substantial potential improvement over existing treatments.

Investors Send Shares Higher

Wall Street immediately recognized the significance.

Definium shares surged in premarket trading Wednesday after the results were released, reversing much of Tuesday’s decline as investors reassessed the likelihood that DT120 could eventually reach the market.

The company also has considerable financial resources behind the program, reporting approximately $1.1 billion in cash, cash equivalents and investments at the end of June.

And anxiety is only one part of the opportunity.

In June, DT120 also produced positive Phase 3 results in major depressive disorder, meaning the same one-dose LSD tablet has now generated successful late-stage results in two of the largest psychiatric treatment markets.

One More Anxiety Trial Matters

Definium still has another major hurdle before it can declare the anxiety program complete.

Its second Phase 3 anxiety study, Panorama, is expected to report results in September.

If that trial also succeeds, Definium could have the pivotal evidence needed to move substantially closer to an FDA submission for generalized anxiety disorder.

That is why Wednesday’s announcement goes well beyond another biotechnology trial result.

For decades, LSD has been known primarily as an illegal psychedelic associated with recreational drug use and the counterculture of the 1960s.

Definium is now attempting to turn a precisely manufactured pharmaceutical version of that compound into something entirely different: a regulated medicine that a patient could potentially take once and experience meaningful relief from severe anxiety within days.

If the remaining trials confirm what Voyage has shown, psychiatry may be looking at the beginning of an entirely new treatment model.

JBizNews Desk | New York

© JBizNews.com All Rights Reserved. Reproduction or distribution without written permission is prohibited.

The Federal Trade Commission is examining Epic Systems Corp., the nation’s largest vendor of electronic health records, for potential violations of antitrust law as part of a broad inquiry into the company’s business practices, according to four people who were recently contacted by investigators.

The probe is in its early stages and may never lead to charges against Epic, whose dominant market position and control of Americans’ health data has rapidly accelerated in recent years. But the people contacted by investigators — who work in or advise health care businesses that interface with Epic — said they were asked about a wide range of issues relating to company policies and practices that have generated continual complaints and lawsuits from former employees and rival companies.


One of the people said the government appears to be pursuing two separate lines of inquiry. One is focused on Epic’s agreements that bar its employees from working for a wide swath of health care businesses that directly, or indirectly, compete with the company. Another set of questions focused on Epic’s use of its dominant market position, and leverage over its hospital customers, to block rival technology companies from getting access to patient data and information needed to support their businesses.

Continue to STAT+ to read the full story…

This post was originally published here. 

The Federal Trade Commission is investigating Epic Systems, the Wisconsin software company whose programs hold the medical records of most Americans, over whether it uses its size to block competitors from reaching patient data. The probe was reported Friday, Aug. 14, citing people contacted by investigators.

Here is what the fight is actually about. When a patient sees a doctor, that visit gets typed into a records system — and for roughly nine out of ten Americans, that system is Epic’s. Epic also runs MyChart, the portal where patients check test results and message their doctor. Because Epic holds the file, Epic decides which outside companies get to read it: a startup that wants to help an insurer process claims, a rival software firm, a new app a hospital wants to try. Competitors say Epic turns that tap on and off to protect its own business. Epic says it is protecting patient privacy and points to the hundreds of millions of record exchanges its customers complete each month, more than half of them with non-Epic systems.

Federal investigators have sent formal demands for information to other companies in the health technology industry, asking specifically how Epic grants or withholds access to data. The inquiry is early, and it may end without any case being brought. The FTC declined to comment.

State authorities got there first. Texas Attorney General Ken Paxton sued Epic in December 2025 under state antitrust law, arguing the company built a gatekeeping position around patient records and shut out challengers. That complaint put the number at more than 325 million patient charts — more than 90 percent of the country. Epic answered on Jan. 20, 2026, calling the claims baseless and saying it would fight for full dismissal, arguing the state’s six-month investigation turned up nothing improper and that the petition leaned on press clippings and borrowed allegations from a private lawsuit.

Two competitors are already in federal court. Particle Health, a data platform, sued in New York claiming Epic made it commercially impossible to operate in the market for insurer-facing tools. CureIS Healthcare filed its own case. As of May 2026, the court in the Particle case had ordered Epic to hand over documents going back to 2021, widening the discovery that any government investigator can now watch closely.

For patients, the practical stake is portability. If a person switches hospitals, moves to another state, or lands in an emergency room across town, whether the new doctor sees the full chart depends on systems talking to each other. Every blocked connection is a blank space in a record someone is treating from.

For hospital executives and the health companies that sell into them, the stake is leverage. Epic is privately held, took in over $4 billion in revenue in 2024, and rarely loses an account once installed — switching costs run into the hundreds of millions for a large system. A federal case, or even the threat of one, is the first real pressure on that arrangement.

What happens next is the harder question. Antitrust investigations of this kind typically run a year or more before the agency decides whether to sue, and the practical fix regulators tend to reach for is not breaking a company up but forcing it to open its interfaces on published, uniform terms — the same access for a startup as for a partner. Federal interoperability rules already push in that direction, and the Texas and Particle cases could produce court-ordered access requirements sooner than Washington, D.C., does. Epic, for its part, says its interfaces are already open, with a public library of more than 500 programming tools and over 1,500 outside apps using them free of charge.

JBizNews Desk | Washington, D.C.

© JBizNews.com All Rights Reserved. Reproduction or distribution without written permission is prohibited.

Every parent experiences a unique mix of emotions when caring for a newborn baby. You’re filled with an overwhelming sense of pride, love, and awe for this tiny, precious person in your arms. There are also feelings of nervousness and anxiety at the sudden responsibility of new parenthood. And, of course, you’re exhausted. There’s no instruction manual to refer to, but you’re in charge, and you’re immediately faced with lots of decisions. And people online are more than eager to tell you what to do and how to do it.

I know this feeling well. I’m a parent myself, but I’m also a pediatrician who has talked to thousands of parents navigating their first days and months with a new baby. After caring for children for more than 30 years, what I can say is that one thing hasn’t changed: Every parent wants to do what is best for their child.

Read the rest…

This post was originally published here. 

NEW YORK — Luigi Mangione pleaded guilty on Friday to federal stalking charges in the killing of UnitedHealthcare CEO Brian Thompson, admitting matter-of-factly that he trailed the executive to an investor conference in 2024 and gunned him down on a New York City street.

Mangione, 28, said he even used a ruse to glean information about the event, contacting the health insurance company ahead of time under the guise of being an investor at a multibillion-dollar firm.

Read the rest…

This post was originally published here. 

Today, we’re looking at a new multiple myeloma approval for Bristol Myers Squibb, PBMs embracing TrumpRx price comparisons, and Novartis winning a key U.K. patent fight over Entresto.

My son built a structurally sound bridge yesterday out of latticed twigs; it supported my weight and also his. It was a moment of great pride. Hire him, he’s 8.

Bristol’s Zenbexus wins accelerated approval in multiple myeloma

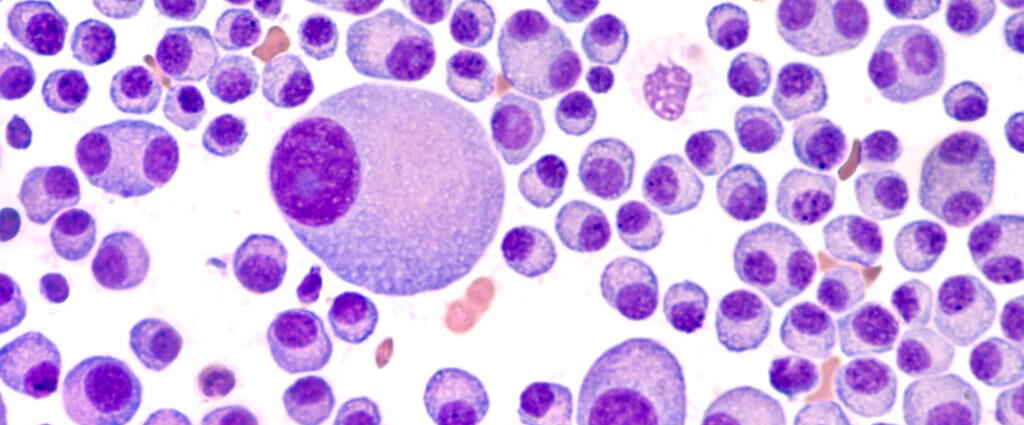
The Food and Drug Administration yesterday approved an oral treatment for advanced multiple myeloma made by Bristol Myers Squibb, marking the debut of a new class of medicine for the blood cancer and the first drug cleared by U.S. regulators using a more sensitive measure of remission.

Continue to STAT+ to read the full story…

This post was originally published here. 

PatientRightsAdvocate.org is challenging the doctor’s association’s copyright of the current procedural terminology, or CPT, system. Use of the codes is required by law, and that means they should be freely available, per the suit.

This post was originally published here. 

And so, another working week will soon come to a close. Not a moment too soon, yes? This is, you may recall, our treasured signal to daydream about weekend plans. Our agenda is still taking shape, but we plan on promenading with the official mascots, catching up on our reading, and hanging with a visiting short person. We also hope to have time for our weekly listening party, where the rotation will likely include this, this, this, this and this. And what about you? As noted previously, this is a marvelous time to enjoy the great outdoors. City streets beckon. And beaches and woodsy trails are closer than you think. You could also curl up with a good book if the weather fails to cooperate, tidy around your castle, or get a head start on back-to-school shopping — the economy could always use a boost. Well, whatever you do, have a grand time. But be safe. Enjoy, and see you soon. …

The U.S. Food and Drug Administration approved an oral treatment for advanced multiple myeloma made by Bristol Myers Squibb, marking the debut of a new class of medicine for the blood cancer and the first drug cleared by U.S. regulators using a more sensitive measure of remission, STAT explains. The drug, which will be sold under the brand name Zenbexus, is part of a Bristol research effort to develop a new and more potent class of blood cancer drugs called CELMoDs that work by redirecting a cell’s natural machinery to eliminate cancer-causing proteins.

A U.S. appeals court ruled that a lower-court judge ‌erred in dismissing a $6.7 billion lawsuit accusing Bristol Myers Squibb of cheating former Celgene shareholders by delaying federal approval for three drugs, Reuters writes. In a 3-0 decision, the appeals court decided UMB Bank was entitled to represent Celgene shareholders as a trustee despite ​an error in how it was appointed. The case arose from Bristol Myers’ purchase of Celgene for $80.3 billion in 2019. Celgene shareholders who ​held “contingent value rights” were entitled to an extra $9 per share in cash if Bristol Myers won timely ​U.S. regulatory approvals for three drugs.

Continue to STAT+ to read the full story…

This post was originally published here. 

A laboratory that tussled with regulators over impurities found in some widely used medicines has accused the group U.S. Pharmacopeia of making false and misleading remarks about its methods for uncovering safety problems.

In a lawsuit filed in a U.S. court, Valisure argued that USP, an independent organization that develops standards for medicines, inaccurately claimed it has used “unvalidated methods” for quality testing that can lead to “misleading results” and “unnecessary concern.”

Valisure maintained USP made these remarks in a 2023 white paper as part of an effort to portray its own testing methods as “inherently and universally safe, while suggesting that other testing approaching undermine public confidence” in medicines. Moreover, the lab alleged USP did so to promote trust in a system that “financially benefits” itself.

Continue to STAT+ to read the full story…

This post was originally published here. 

The Food and Drug Administration on Thursday approved an oral treatment for advanced multiple myeloma made by Bristol Myers Squibb, marking the debut of a new class of medicine for the blood cancer and the first drug cleared by U.S. regulators using a more sensitive measure of remission. 

The Bristol drug, iberdomide, will be sold under the brand name Zenbexus. It will be used in combination with two other drugs, Darzalex and dexamethasone, to treat patients with multiple myeloma who have received at least one prior line of therapy. 

“With the Zenbexus approval, Bristol is the first company to bring a novel class of drugs to patients with multiple myeloma, opening venues for many more potential combinations,” said Cristian Massacesi, Bristol’s chief medical officer, in an interview with STAT ahead of the approval announcement. 

Continue to STAT+ to read the full story…

This post was originally published here. 

Cleveland Clinic is now sending prescriptions to patients by air. A pharmacy technician at its Beachwood campus loads a filled order into a secure drop box, an autonomous drone picks it up, flies to the patient’s address, hovers roughly 300 feet overhead and lowers the package to the ground on a tether. The drone never lands. The pod sets the medication down, winches back up, and the aircraft returns to its charging station.

The service went live Monday, Aug. 3, and has been running daily since. Cleveland Clinic says it is the first long-term deployment of a prescription drug drone delivery program by a U.S. health system, which is the distinction that matters commercially — hospitals have flown medical drone pilots for years, but this one is built to operate as a standing part of patient care rather than a demonstration.

The operator is Zipline, the drone logistics company that has been flying medical payloads since 2016. The company has delivered tens of millions of medical products worldwide and now serves more than 5,000 hospitals and healthcare facilities, and says each aircraft runs more than 500 safety checks every second in flight.

The launch is deliberately small. Deliveries are limited to patients within a five-mile radius of Cleveland Clinic’s Beachwood Administrative Campus, which serves as the drones’ home base. Eligible patients are those already enrolled in the health system’s pharmacy home delivery program; the pharmacy team notifies them through their patient portal when a medication qualifies. The option is voluntary and carries no extra charge.

What flies is limited too. Controlled substances are not being transported by drone at this stage, and refrigerated items are excluded, leaving shelf-stable prescriptions as the initial payload. Patients follow the aircraft through a tracking link sent in the MyChart portal.

The operating case is speed. Matt Soder, executive director for Cleveland Clinic specialty and community pharmacies, said a courier run traditionally takes several hours from notification to the patient’s door, where the drone route is measured in minutes. For a patient starting an antibiotic or waiting on a refill, that compresses a same-day errand into a wait shorter than the drive to the pharmacy would have been.

Volume showed up immediately. Bri Robinson, who manages the health system’s home delivery pharmacy, said on launch day that the pharmacy opened at 7 a.m. and had already sent five to ten orders to patient homes.

Lindsey Amerine, chief pharmacy officer at Cleveland Clinic, framed the program as an extension of the system’s existing delivery operation rather than a standalone experiment, saying it strengthens home delivery and extends the reach of its services beyond the walls of its facilities. Zipline’s president of U.S. healthcare, Hillary Brendzel, made the customer argument in plainer terms: one less errand to run, and more time back in people’s days.

For the healthcare business, the economics sit in the last mile. Pharmacy home delivery has been growing for years, but it is carried by courier fleets and parcel networks whose costs scale with drivers, vehicles, fuel and traffic. An autonomous aircraft that completes a short hop in minutes and returns to a charging station changes that cost curve, and it changes what a health system can promise a patient about timing. That is why the first long-term deployment matters more than any of the pilots that preceded it — a program designed to run indefinitely has to survive on its unit economics, not on grant funding or novelty.

The expansion path is already mapped. Cleveland Clinic plans to add locations and to use the drones for additional medications, lab samples, medically tailored meals and medical supplies. Lab samples are the item to watch: moving specimens between collection sites and central labs is one of the most routine, most vehicle-dependent logistics problems in medicine, and it is the kind of repetitive short-distance run that autonomous aircraft handle best.

Regulation remains the gate on how fast any of this scales. Routine flights beyond a pilot’s visual line of sight require federal approval, and Cleveland Clinic and Zipline say they cleared the regulatory and technical requirements before launching. Every new service area will need the same clearances, which is why a program of this kind starts inside a five-mile circle rather than across a metropolitan region.

For now, the practical picture is narrow and real: a few thousand households on Cleveland’s east side can have a prescription arrive in the yard in minutes, and the rest of American healthcare is watching whether the numbers hold up well enough to copy.

JBizNews Desk | Cleveland

© JBizNews.com All Rights Reserved. Reproduction or distribution without written permission is prohibited.

The Trump administration’s campaign to eradicate transgender health care for young people has run into a series of legal roadblocks: Judges have ruled against Justice Department subpoenas, a declaration from the health secretary, and parts of the president’s executive order halting all federal support for this care. But a new rule finalized this week by the Centers for Medicare and Medicaid Services may prove more difficult to challenge. 

The agency announced Tuesday it was barring the use of federal Medicaid and CHIP dollars to pay for pediatric gender-affirming medications and surgery. Then on Thursday, the Department of Health and Human Services released a report on diagnostic coding practices among gender-affirming care clinicians and referred hundreds of health care groups to the Justice Department for investigation into those practices. Despite many court losses, the administration has successfully pressured at least dozens of hospitals into closing or pausing gender-affirming care programs. 

Read the rest…

This post was originally published here. 

After doing three loops around the parking lot, you finally see a free spot. You step on the gas to claim it, but an SUV cuts in front of you and steals the space. You stomp on the brakes, jerking to a halt. You might forgive the other driver, but your Toyota remembers.

Later, as you drive home, your eyes wander to the restaurant that just opened on the corner. Your car loudly beeps you back to attention, the dashboard scolding, “keep eyes on the road.” Your car is watching you, and that hard stop and brief glance to the side are data sent directly to your car insurer, churning into an algorithm that decides your future premiums.

Read the rest…

This post was originally published here. 

At a church on the outskirts of Liverpool, older residents amble in for community lunch. In Sunderland, mothers swap stories as they are guided through play exercises with their babies at a local hub. On the St Matthew’s estate in Leicester, children spill out of school and onto a new football pitch.

These scenes are unremarkable, the everyday rhythms of community life. None of it looks much like health care. But this relational, daily support keeps people healthy and resilient outside of the clinical system — while remaining largely peripheral to how we fund, measure, and debate health.

Read the rest…

This post was originally published here. 

Commure, a $7 billion health software company that sells artificial intelligence tools to medical clinics, has terminated a program through which it was paying parties for referrals to new customers, according to company emails obtained by STAT. 

The emails, sent by Commure’s chief legal officer, Dan Brian, inform members of the partnership program that their payment agreements will be terminated 30 days from receipt of the company’s notice. One email, dated Aug. 6, states that anything owed under the agreement as of the termination date will be “paid in full.”

The notice was sent to members of the program six days prior to the publication of a STAT investigation that found the company offers to pay thousands of dollars to customers and other parties to refer its AI products to new business prospects. STAT first asked about the referral arrangements in an email to Brian on June 5.

Continue to STAT+ to read the full story…

This post was originally published here. 

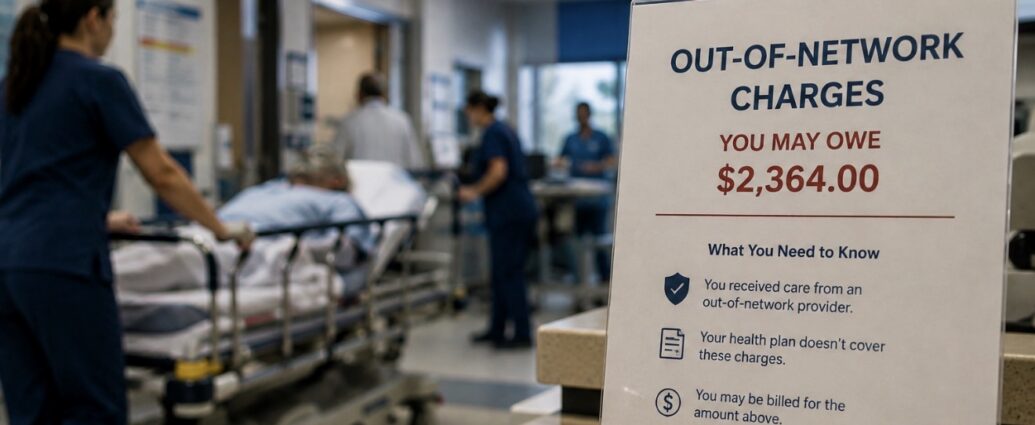
The full 17-judge Fifth U.S. Circuit Court of Appeals ruled Tuesday that the government’s method for calculating the benchmark rate at the center of the No Surprises Act is partly unlawful, siding with the Texas Medical Association on two of its three challenges. Patients are not affected. The protection that keeps you from getting an out-of-network bill after an emergency room visit stays exactly where it was. What changed is the number insurers and doctors argue over once the patient is out of the picture.

That number is the qualifying payment amount — roughly, the median in-network rate for a service in a given area. When a patient is protected from being billed directly, the doctor and the insurer go to arbitration, and the arbitrator weighs each side’s offer against that benchmark. Set it low and the insurer pays less.

The court found insurers had been allowed to pad the calculation with “ghost rates” — contracted prices for services a provider never actually performs. Because nobody bothers negotiating a rate for work they don’t do, those numbers can sit at almost nothing. The government told insurers not to count rates of $0, but a contracted rate of $1 was permitted. The judges also found the government wrongly ordered insurers to leave out bonus, penalty and other incentive-based compensation, which the law requires the benchmark to capture. On the third question, the court agreed with the government: one-off single-case agreements, common in air ambulance billing, stay out of the calculation.

The math behind the fight explains why this matters. Providers or their representatives filed roughly 3 out of every 4 disputes in the second half of 2025, and won about 85% of them — roughly 6 out of every 7 cases that reached a decision. Awards came in above the insurer’s benchmark 87% of the time. In the fourth quarter alone, arbitrators issued 532,548 payment determinations, and 462,973 of those landed above the benchmark — about 7 in every 8. The judges pointed to those lopsided win rates as evidence the benchmark had been set too low.

The volume is enormous and growing. Nearly 1.4 million disputes were initiated in the second half of 2025, on top of close to 1.2 million in the first half — roughly 2.6 million in a single year. Providers collected close to $15 billion through the process in 2025, up from about $4.1 billion in 2024, nearly a fourfold jump.

The payouts themselves run well above ordinary rates. Doctors who win these determinations are often awarded three or four times the comparable in-network rate. In one case, a plastic surgeon received $440,000 for a breast reduction that normally runs $15,000 to $25,000 — roughly twenty times the going rate.

Insurers argue the win rates prove providers are gaming a system built for rare disputes. Doctors argue the opposite: that the win rates prove insurers were lowballing all along, and that a benchmark stuffed with prices for phantom services was never a fair yardstick. Tuesday’s ruling accepts the doctors’ version.

The court did not blow up the system on its way out. It vacated the methodology but said the agencies may let insurers keep using existing benchmark figures until new ones can be calculated, so arbitration can continue without interruption. The Health and Human Services, Labor and Treasury departments now have to rewrite the rules to match the statute, and could appeal.

For business owners, the exposure sits in the health plan, not the doctor’s office. Higher awards flow to insurers’ commercial books, and the companies are expected to pass those costs to employers and patients through premiums. Regulators finalized a rule this spring aimed at some of the arbitration process’s problems, including the volume of ineligible disputes clogging the queue, though insurers said it did not go far enough — non-initiating parties challenged the eligibility of 42% of disputes filed against them in the second half of 2025, better than 2 in 5.

The reform that would matter most is not another rule about who can file. It is getting the benchmark itself right, which is precisely what the court just ordered. A number built from prices for services that were actually delivered, including the bonus payments doctors really earn, gives both sides less reason to arbitrate in the first place. Fewer disputes means less administrative cost baked into premiums.

Whether the agencies produce that number quickly is the open question. Until they do, the arbitration machine keeps running on the old figures, and employers keep paying for the argument.

JBizNews Desk | New York

© JBizNews.com All Rights Reserved. Reproduction or distribution without written permission is prohibited.

You’re reading the web edition of D.C. Diagnosis, STAT’s twice-weekly newsletter about the politics and policy of health and medicine. Sign up here to receive it in your inbox on Tuesdays and Thursdays.

Every competitor got a gold medal at Trump’s Freedom 250 Patriot Games, which sounds more like Lake Wobegon than an elite youth sports event. Send news tips and stories about your above-average kids to John.Wilkerson@statnews.com or John_Wilkerson.07 on Signal.

Kennedy goes west

The day after the White House made another big push to change how Americans get vaccines, health secretary Robert F. Kennedy Jr. was in California pushing to change addiction treatment — and blaming the prior administration for how it previously handled it. My colleague Chelsea Cirruzzo was there with him.

Continue to STAT+ to read the full story…

This post was originally published here. 

Want to stay on top of the science and politics driving biotech today? Sign up to get our biotech newsletter in your inbox.

There’s limited access to California’s cheap insulin, Eli Lilly’s cracking down on black market retatrutide, and new biotech Khartis Therapeutics emerges with $95 million.

Some rather buff fellows at my gym were comparing abdomens today, raving about the bodysculpting wonders of all that illicit “reta.” I imagine they won’t be too pleased about the Lilly news.

Continue to STAT+ to read the full story…

This post was originally published here. 

Rise and shine, everyone, another busy day is on the way. And it is getting off to a pleasant start here on the Pharmalot campus, where clear blue skies and comfy breezes are greeting us. As for the official mascots, they are happily snoozing in their respective corners. As for us, we are firing up the trusty kettle for another cuppa stimulation. Our choice today is ginger peach. And here is a helpful tip — a teaspoon of honey enhances the flavors splendidly. Of course, you are invited to join us. For the full experience, we are now hawking replicas — take a look. Meanwhile, here are a few items of interest. As always, do keep in touch. We appreciate feedback, criticism, and tips. …

Novo Nordisk chief executive officer Mike Doustdar believes investors are underestimating the demand for differentiation among obesity drugs, ‌and that new treatment options like pills will keep it from becoming a winner-take-all battle with rival Eli Lilly, Reuters writes. Novo was first to bring a highly effective GLP-1 weight loss injection, Wegovy, to the U.S. market, but is under pressure to regain ground lost to Lilly’s Zepbound in a business that ​analysts expect will be worth more than $100 billion a year by 2030.

Drugmakers are holding back applications for health insurance coverage in Switzerland over concerns that lower prices there could affect their U.S. ​business under drug-pricing policies introduced by the Trump administration, Reuters says, pointing to a new survey. About one-third of new innovative medicines were not submitted for coverage under Switzerland’s mandatory health insurance system between January 2025 and June 2026, potentially limiting patient access to new ​treatments, saccording to the survey ​by Interpharma.

Continue to STAT+ to read the full story…

This post was originally published here. 

You’re reading the web edition of STAT’s Health Tech newsletter, our guide to how technology is transforming the life sciences. Sign up to get it delivered in your inbox every Tuesday and Thursday.

Hello, health tech readers! Next week, the newsletter is going on its annual summer hiatus — we’ll see you back on the 25th.

Today, a deep dive into Commure, a company promising to automate the business of health care with artificial intelligence — and all the levers it’s pulling to make that happen. Let’s get right into it.

Continue to STAT+ to read the full story…

This post was originally published here. 

This story first appeared in Adam’s Biotech Scorecard, a subscriber-only newsletter. STAT+ subscribers can sign up here to get it delivered to their inbox.

A drug for a rare disease is evaluated in a small clinical trial. The treatment is modestly effective with manageable side effects. Balanced against the devastating nature of the disease, the drug is benefiting patients more than it is causing harm. Regulators approve it.

Months later, physicians prescribing the drug widely start to note a small number of patients are dying, despite the fact that no deaths were reported in a clinical trial of the drug. Similarly, the frequency of serious side effects rises dramatically, including some so severe that patients require hospitalization. The drug’s real-world safety profile appears worse than what was characterized in the small clinical trial.

Continue to STAT+ to read the full story…

This post was originally published here. 

Scroll through the flashy websites of neurotechnology startups and a phrase repeats again and again: “minimally invasive.”

“The term is fuzzy, problematic,” said Anna Wexler, a medical ethics and health policy professor at the University of Pennsylvania Perelman School of Medicine. “Is it physical invasiveness? We’re not sure, it’s a fraught term.”

The fuzziness hasn’t stopped most brain-computer interface startups from deploying it in a bid to differentiate their devices from others in development. Synchron, Motif Neuroscience, Precision Neuroscience, and Merge Labs all use it liberally. Journalists sometimes repeat the spin.

Continue to STAT+ to read the full story…

This post was originally published here. 

For hospitals, the promise of artificial intelligence is financial as much as clinical. A hospital might deploy an AI device because it promises to throw up an alert that could save a patient’s life — but the technology is far more likely to stick if it proves it can drive down costs. 

Convincing hospitals and health systems that a new technology will provide that return on investment is tricky, though. So some AI startups have benefited from a temporary sweetener that helps customers get on board: Certain new technologies can apply to get add-on payments from Medicare for two or three years after they come to market. The tax-dollar-funded payments are meant as an incentive to help get new, expensive medical technologies to patients.

If a hospital thinks, “‘Oh, you’re not 100% sure you have the money, or you don’t necessarily believe 100% of the assumptions in the ROI,’ then you know what? You have this safety net, at least for the next few years,” said Tom Valent, chief business officer at Aidoc. 

Continue to STAT+ to read the full story…

This post was originally published here. 

I have spent much of my career responding to infectious diseases in places where vaccines were desperately needed but not always available.

In Haiti, I watched a patient die of tetanus, their body seized by violent, agonizing spasms until they could no longer breathe. Watching someone die that way from a disease a simple vaccine can prevent is something I have never forgotten.

Read the rest…

This post was originally published here. 

Over the last several years, fearmongering about statins has exploded, as misinformation alleges that they damage the brain, liver, and muscles, among other problems.

Oxford researchers recently published a study in the Lancet Digital Health that should help with one common concern involving muscle disorders. Whether it ultimately does, however, will tell us a lot about the influence of online misinformation, and the scientific community’s ability to counter it.

Read the rest…

This post was originally published here. 

Shortly after her wedding four years ago, Jenilee Crowley felt ready to start having kids. Then the 38-year-old found a lump in her breast that upended all her future plans.

Chemotherapy, radiation, and other cancer treatments come with a slew of side effects, including hormone changes and potential organ damage that can risk a person’s fertility.

But Crowley, who was diagnosed with stage one breast cancer in 2022, learned that she had options. After a double mastectomy to remove the cancer, Crowley started hormone therapy to help prevent it from returning. Then, under medical guidance from her team at Dana-Farber Cancer Institute, she paused the treatment so that she and her husband could freeze embryos and try for a baby. Her son, Archer, is now four months old.

Continue to STAT+ to read the full story…

This post was originally published here. 

STAT is co-publishing this article by KFF Health News.

SAN FRANCISCO — At a Walgreens in this city’s bustling Japantown neighborhood, pharmacist Margaret On stocks two boxes of long-acting insulin pens from California’s new prescription drug label, CalRx, emblazoned with the state’s iconic grizzly bear.

Although she hasn’t dispensed any, On plans to keep them on hand. “It’s good to have if a patient comes in and doesn’t have health insurance,” she said. “Or just in case of emergencies.”

Continue to STAT+ to read the full story…

This post was originally published here. 

The Trump administration on Wednesday unveiled a new framework for helping Americans facing the often-intertwined circumstances of addiction and homelessness. 

In a new toolkit, the White House unveiled a “treatment first” model that boosts faith-based interventions while rejecting harm reduction principles and the “housing first” strategy that characterized the Biden administration’s approach. While the new strategy favors medicalized approaches to treating addiction, it cites abstinence as the ultimate goal as opposed to also celebrating decreased drug use and related harms. 

Read the rest…

This post was originally published here. 

A highly anticipated No Surprises Act court decision delivered yet another win for providers, finding that the government erred in its instructions for calculating the amounts health insurers typically pay for services.

Tuesday’s decision from the U.S. Court of Appeals for the Fifth Circuit stems from a 2022 Texas Medical Association lawsuit challenging the government’s rule for calculating the qualifying payment amount, a number that’s used in arbitration to represent health insurers’ contracted rates for services. The trade group for doctors had argued that the methodology yielded numbers that were unfairly low, and the court mostly agreed.

The Fifth Circuit sided with providers against the federal government on two of three points: that the QPAs should not include so-called ghost rates, or placeholder rates that providers don’t actually negotiate, and that they should include bonus and incentive payments. It disagreed with air ambulance providers, finding that a one-off price for transporting a single patient should not factor into QPAs. 

Continue to STAT+ to read the full story…

This post was originally published here. 

Young adults’ use of vapes and cannabis hit all-time highs last year, according to the results of a large new national survey conducted at the University of Michigan.

The percentage of young adults who said they’d used nicotine vapes in the past 30 days reached the highest levels since the question was first added to the survey in 2017, more than tripling to 19%. For cannabis, 29% of young adults between the ages of 19-30 said they’d used the drug in the past 30 days — just slightly below the all-time high of 30% the previous year. A record high of 12% reported daily cannabis use. 

The annual Monitoring the Future survey, which is supported by the National Institutes of Health, gathers data from about 20,000 Americans spanning the ages of 19 to 65. Overall, this year’s report presents a mixed picture of substance use trends in the U.S, according to Nora Volkow, director of NIH’s National Institute on Drug Abuse (NIDA).

“It is reassuring to continue to see relatively low smoking rates and a continuing decline in alcohol use among adults,” Volkow said in a press release. “At the same time, rising rates of cannabis, nicotine, and certain other drug use warrant attention. Continued monitoring is vital for understanding the changing drug landscape so that we can develop effective interventions to support public health.”

Read the rest…

This post was originally published here. 

Talks are underway between authorities in the Democratic Republic of the Congo and the World Health Organization to expedite the start of a multi-armed Phase 3 clinical trial of vaccines geared towards helping to contain spread of the Bundibugyo virus in the northeast of the country, which the director-general of the global health agency warned Wednesday is on track to become the largest Ebola outbreak on record.

“It’s already the second-biggest Ebola epidemic on record, and it’s moving faster than any previous Ebola outbreak. At its current pace, it’s on track to eclipse the West African Ebola outbreak of 2014 to 2016,” Tedros Adhanom Ghebreyesus said during a news conference in Geneva. 

Read the rest…

This post was originally published here. 

Senior officials of the World Health Organization, including Director-General Tedros Adhanom Ghebreyesus, criticized the Trump administration’s newest attempt to trigger an overhaul of U.S. vaccination policy on Wednesday, calling it politically motivated and contradictory to the best available science.

The critique was aimed at an executive order signed by President Trump on Monday. It calls for a reduction in the number of vaccinations recommended for all children in the U.S., and for the use of vaccines targeting single pathogens rather than the combination vaccines now in use, starting with the measles, mumps, and rubella shot.

Read the rest…

This post was originally published here. 

President Trump signed an executive order Monday directing that the measles, mumps and rubella vaccine be given as three separate shots — a product that does not exist in the United States, has not been manufactured here in more than fifteen years, and that the company making the combined version says it sees no reason to build.

Merck discontinued its standalone measles, mumps and rubella vaccines — Attenuvax, Mumpsvax and Meruvax II — in 2008, and told the CDC’s Advisory Committee on Immunization Practices in 2009 that it would not resume production. That was a demand decision rather than a safety judgment: the advisory committee had settled on combination shots, and the single-antigen versions had virtually no market. Reviving them is not a matter of restarting a line — manufacturers would need new clinical trials, reconfigured facilities and three separate FDA approvals.

Merck said its combined vaccine is supported by decades of clinical and real-world evidence, and that separating the shots could result in delayed or missed immunizations. GSK also makes an MMR vaccine, and splitting the product would be expensive and complicated for both companies.

The order conditions the MMR provision on such products becoming domestically available and gives the Department of Health and Human Services 90 days to present plans for offering single vaccines, including by working with the private sector and other countries. The instruction to spread immunizations across separate visits is qualified with language about doing so to the maximum extent feasible.

The order also recommends removing seven vaccines from the childhood schedule except for certain high-risk groups, narrowing it to shots covering 11 diseases. The administration signaled it will press states to rewrite their vaccine requirements to match the new federal guidance.

The document itself never uses the word autism; that connection came from Trump’s spoken remarks at the signing rather than the text. Speaking from the Oval Office flanked by health officials including HHS Secretary Robert F. Kennedy Jr., Trump said the administration was reducing the number of shots and spacing them across more visits, and suggested at one point that the MMR shot can be “quite lethal.” The CDC’s own guidance states there is no published scientific evidence showing any benefit to separating the combination MMR into three individual shots, and that receiving the vaccine is much safer than contracting the diseases. Two doses are 97% effective at preventing measles, according to the agency.

The pushback came from the president’s own party as well as the medical establishment. Senator Bill Cassidy, the Louisiana Republican who chairs the Senate Health Committee and is a physician, said breaking up vaccines would mean children need more shots for the same protection, not fewer, and would increase hesitancy. Cassidy cast the deciding vote to confirm Kennedy, saying at the time that Kennedy had promised not to change the childhood schedule. The American College of Physicians called the order part of a pattern of attempting to change vaccine guidance unilaterally rather than through transparent scientific review. American Academy of Pediatrics President Andrew Racine said the order does nothing to support families of children with autism.

This is not the administration’s first attempt. Under Kennedy, the CDC already cut shots covering six of 17 diseases from the schedule, only to have the move blocked in federal court, and at least 28 states have refused to accept the changes and are holding to the earlier recommendations. The judicial stay came in March. The AAP has continued publishing its own schedule, and the American Academy of Family Physicians issued 2026 schedules in March aligned with it.

The commercial stakes reach well past Merck. Manufacturers with meaningful exposure to routine childhood immunization revenue include Pfizer, Moderna, BioNTech, GSK, Sanofi and Merck. Sanofi is among the largest U.S. childhood vaccine suppliers through its DTaP combination products, and its shares were already down 11.2% year to date before the order; Moderna fell 4.28% on the session when Bloomberg first reported the order was under consideration on Aug. 6. The near-term risk for these companies is less about mandates than uptake — public confidence drives volume, and a fragmented schedule requiring more appointments historically produces lower completion rates.

The timing is what makes the disease math uncomfortable. The CDC counted 2,371 confirmed measles cases through July 30 across 34 outbreaks, already exceeding all of 2025 and making this the worst measles year in more than three decades, with Utah’s outbreak topping 500 cases. A national verification committee is reviewing U.S. measles elimination status this month, and the Pan American Health Organization is scheduled to rule in November on whether the country still qualifies as free of endemic transmission — a designation held since 2000.

For parents, there is unlikely to be an immediate change in vaccine access, and the order is expected to draw legal challenges.

JBizNews Desk | Washington

© JBizNews.com All Rights Reserved. Reproduction or distribution without written permission is prohibited.

Waiting for treatment to start can be an excruciating period for cancer patients. There can be fears that the disease is spreading, or progressing to a point where therapies become less effective. Yet over the last few decades, the time cancer patients are waiting between diagnosis and treatment has steadily grown, according to a new study of more than 2.7 million patients.

“What was striking was the consistency,” said Tim Donahue, the senior author on the study and a surgical oncologist at the University of California, Los Angeles. “Across every cancer we studied, patients are waiting longer today than they were a decade ago.”

Donahue and his colleagues analyzed data from the National Cancer Database, a national data repository from the American College of Surgeons, from 2012 to 2023. They looked only at patients with stage 1 to 3 cancers that were considered eligible for surgery at diagnosis across six different cancers. Then, they compared the time between diagnosis and any first treatment, which included surgery as well as radiation or chemotherapy or other medical therapies. 

Continue to STAT+ to read the full story…

This post was originally published here. 

The Lindsay Clancy case has become one of the most painful and polarizing stories in recent American memory. At its center are the unimaginable deaths of three young children and a mother whose mental state has become the subject of intense legal, medical, and public scrutiny. The criminal justice system will determine legal responsibility, but regardless of the trial’s outcome, the case exposes a larger and uncomfortable truth: Our understanding and treatment of postpartum psychiatric illnesses remain profoundly inadequate.

For many observers, the debate has become a binary one. Either Clancy was suffering from a severe postpartum psychiatric disorder, or she was not. Either she is guilty of murder or she is not. Either the system failed her or it did not. And, despite numerous attempts to seek medical care, she was either inappropriately medicated or not.

Read the rest…

This post was originally published here. 

The libertarian think tank analyzed almost 130 studies digging into the controversial laws, which require providers to get state approval before building facilities or adding new services. What it found wasn’t good.

This post was originally published here. 

Hello, everyone, and how are you today? We are doing just fine, thank you, especially since the middle of the week is upon us. After all, we have made it this far so we are determined to hang on for another couple of days. And why not? The alternatives — at least those we can identify — are not so appetizing. And what better way to make the time fly than to keep busy. So grab that cup of stimulation and get started. Our flavor today is butter pecan, a pantry favorite. We hope you have a lovely day, and do keep in touch. …

A group of physicians and experts in Prader-Willi syndrome, a rare disease that causes an insatiable desire to eat, notified clinicians of a series of patient deaths and cases of severe side effects potentially associated with Vykat XR, a newly approved drug sold by Neurocrine Biosciences, STAT reports. Vykat was approved by the U.S. Food and Drug Administration last year, but since then, seven people prescribed the drug have died, according to the FDA’s Adverse Event Monitoring System. And more than 100 reports of serious adverse events, mostly cases of patients hospitalized for swelling, respiratory, and heart complications, have been reported to the FDA. 

Eli Lilly filed six lawsuits against U.S. companies it accuses of illegally selling black-market versions of its experimental obesity drug retatrutide, escalating its campaign against unauthorized sellers before the medicine has won regulatory approval, Reuters says. The drugmaker said the lawsuits target a ​range of businesses, including compounding pharmacies, medical spas, and online sellers that allegedly marketed retatrutide ​products to consumers despite the drug remaining under clinical development. Retatrutide is still in ⁠Phase 3 clinical trials for obesity, type 2 diabetes, and other related conditions.

Continue to STAT+ to read the full story…

This post was originally published here. 

James “J.P.” Holland is taking the reins of Humana’s Medicaid business, a key growth area for the company, starting this coming Monday. It’s part of a broader leadership transition announced late last year.

This post was originally published here. 

The company says its patient portal should help translate medical jargon into plain language. It’s Oracle’s latest move to stand out in the competitive EHR market.

This post was originally published here.